Four Hours on a Retractor

Updated: Sep 9
Cut to the Chase: General Surgery Survival Series — Post 05
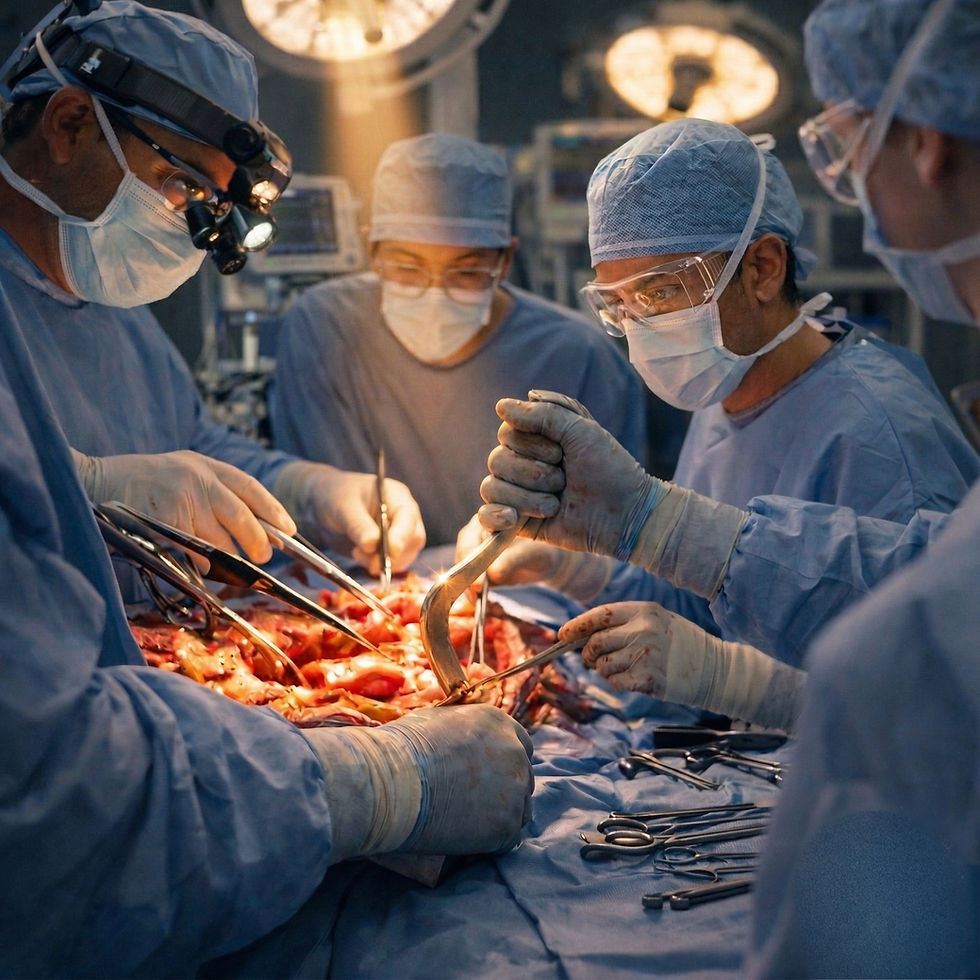
Nobody tells you this early enough, but the retractor is often the best seat in the house. You work that out sometime after your shoulder has started hating you.
The first part is physical. Forearm tightens, fingers go a little numb, you shift your weight and hope nobody noticed. Then somewhere around hour two it turns into something else, and you start wondering whether this is all you’re here to do.

Here are the two questions that change the next four hours. What are we trying to expose, and what are we trying not to injure?
You don’t need attending-level anatomy to answer them. You need a rough answer to both, and then you’re not pulling on something, you’re holding open the thing he’s trying to see.
Ask both of those before the drapes go up, or at the first pause. Most attendings will answer at length, and nobody has ever thought less of somebody for asking.
A lot of trainees spend four hours on a retractor and walk out thinking all they did was stand there. Usually that means they were in the room and not in the case.
From that spot you see where planes open cleanly and where they don’t. You see what gets protected before anybody says a word about it. You see the rhythm of a surgeon who’s done this enough times that the case looks quieter than it actually is.
Watch the operator’s hands instead of your own. Yours aren’t doing anything you need to think about, and his are the entire lesson for the next three hours.
Early on, everybody wants to skip to doing. Drive camera, cut suture, tie knots. Fair enough. But first you learn how a case looks, then how it feels, then when it’s starting to go sideways, and only after that do your hands start to make sense.
Observation is work. Follow the case as it moves: what got opened, what got mobilized, what nearly became a problem.
What gets in the way is that you’re busy wondering how you look. Whether you’re in the way. Looking lost. Getting pimped. Passing out. So you stand there holding metal and running a private toughness ritual while the actual lesson is happening six inches in front of you.
Nobody hands out medals for forearm ischemia.
What I’m watching from the other side of the table isn’t whether you can suffer quietly. I’m watching whether the field stays open, whether you hear a small correction and make a small correction, and whether you can tell where the dissection is headed before somebody has to narrate it for you.
I lost a field once as a second-year, on a redo colectomy that had been going about three hours. My hand had been going numb for twenty minutes and I hadn’t said anything, because he was somewhere in the case he didn’t want to be interrupted in.
Then the retractor slid maybe half an inch and the plane he’d spent forty minutes developing closed back up.
He didn’t say anything to me about it. He reset it himself and kept going, and it cost the case about ten minutes. What I’ve never gotten past is that it was ten minutes I could have bought back with six words, twenty minutes earlier.
Say it while it’s still a small problem. “My hand is cramping, can I switch” is six words, and the version where you wait costs the room ten minutes.
Don’t drift because you’re tired. Don’t make a huge correction when somebody asked for a small one. And say it early: “My hand is cramping, can I switch.” “I’m getting lightheaded, I need to step back.”
That reads as judgment. This is a workplace, not a hazing ritual. What creates tension is a trainee getting tired silently, into a field somebody is working inside.
Eat before a long case and keep your knees soft.
And don’t misread silence. If nobody’s talking to you, the room is working. Nobody has time to turn a long case into a seminar for your comfort.
There’s a point in most long cases where you either check out or check in. The ones who check out start thinking only about their own discomfort. Their pull drifts. They stop seeing the field.
The ones who check in start reading the case from inside it, and the difference is visible from across the table.
One more thing about the pulling itself. Steady tension, not maximum force. You aren’t trying to impress the fascia.
So if you spend four hours on a retractor and walk out thinking you just stood there, that’s probably not true. You learned what a case feels like once it stops being exciting and starts being work. You learned anatomy the way it actually appears rather than the way it sits in an atlas. You learned whether you can stay useful without being the center of the room.
Some case in the next month somebody will ask what happened in there, and you’ll be able to tell them, not just that it was an ex lap and your hand hurts. Nobody will make anything of it. Then you’ll go see what’s next on the board.
What to Read Next: Post 06, “Stop Giving Data Dumps.” You’ve spent four hours learning to see a case. Next you have to say what you saw, in about thirty seconds, to somebody who is still scrubbing.


Comments